
The Biology Behind Skin Color
How Melanocytes Produce Pigment
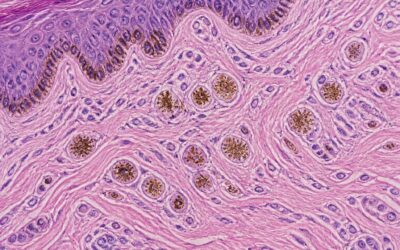
The sheer diversity of human skin pigment is one of nature’s most profound spectacles, yet its genesis occurs within microscopic factories. At the base layer of our epidermis reside melanocytes, the specialized cells responsible for this chromatic variation. These cells manufacture melanin, a complex polymer that determines our skin’s hue. The process, known as melanogenesis, is orchestrated by the enzyme tyrosinase, which oxidizes the amino acid tyrosine to initiate pigment creation.
This biosynthetic pathway is influenced by multiple factors, but ultraviolet radiation acts as the primary catalyst. When exposed to the sun’s rays, melanocytes increase production, a biological defense mechanism often perceived later as a tan. Consider the central steps of this complex process:
1. UV exposure triggers a DNA damage response within skin cells.
2. This activates the melanocortin 1 receptor on melanocytes.
3. The receptor stimulates tyrosinase activity for melanin synthesis.
4. Mature melanin granules are transported to keratinocytes via dendrites.
The resulting skin pigment granules, referred to as melanosomes, accumulate above the nucleus of keratinocytes. This placement creates a physical shield, protecting DNA from harmful mutation. Interestingly, the quantity, size, and distribution of these granules matter more than the sheer number of melanocytes, as all individuals possess a similar density of these cells.
Within this system, two distinct forms of melanin exist: eumelanin, which produces brown to black tones, and pheomelanin, which yields red and yellow hues. The ratio of these molecules determines an individual’s basal skin pigment profile. This biological machinery is a testament to evolutionary adaptation, intricately tuned to geographic ancestry and historical UV exposure levels. In South Africa, with its high UV index, this evolutionary legacy is particularly visible in the rich variations across our diverse populations. This delicate equilibrium between photoprotection and vitamin D synthesis underscores the intricate sophistication of human biology.
The Role of Genetics in Baseline Complexion
The baseline of human skin pigment is determined by inherited variations in genes that regulate melanin production. The MC1R gene holds particular influence, as certain alleles reduce eumelanin output and increase pheomelanin, producing lighter or redder complexions. This genetic instruction set differs across populations, which explains why geographic ancestry so strongly predicts baseline pigmentation.
Gene expression also plays a role. Variants in SLC24A5 and TYR alter the amount of melanin synthesized per cell, sometimes by a single amino acid change. These small molecular shifts lead to wide observable differences. In South Africa, families often display diverse pigmentation within the same household, because recessive and dominant alleles recombine in each child. The resulting baseline is not fixed; it is a dynamic genetic outcome shaped by thousands of years of migration and adaptation.
Pigment vs. Pigmentation: Understanding the Difference
The science of skin pigment is often misunderstood, and one of the greatest misconceptions lies in the distinction between the substance itself and the process that creates it. People frequently use the terms interchangeably, but they refer to different biological phenomena. This difference is crucial for understanding how complexions function under the unique South African sun.
Skin pigment is the physical material, specifically the melanin molecules residing in the epidermis. It is the finished product, the static compound that absorbs ultraviolet radiation. Pigmentation, however, is the dynamic biological process. It encompasses the synthesis of that melanin, its transportation to the keratinocytes, and the distribution pattern across the skin. It is a cellular workflow, not a fixed substance.
– Pigment is the chemical compound; it is the result.
– Pigmentation is the mechanism; it is the reaction.
– Pigment determines the color of the skin at rest.
– Pigmentation dictates how the skin responds to UV exposure.
The process of pigmentation can be triggered by hormonal shifts or sunlight, leading to a temporary or permanent change in the amount of skin pigment. While the baseline pigment is constitutional, the process of pigmentation is responsive and variable, reacting to the environment to create the final visible tone. This is why two people with similar base colors can tan so differently.
Common Triggers for Uneven Skin Tone
Hormonal Fluctuations and Melasma
Hormonal fluctuations are the most persistent instigators of uneven tone, particularly in South Africa’s intense UV environment. During pregnancy, oestrogen and progesterone can hyperactivate melanocytes, causing them to deposit excess skin pigment in a symmetrical mask across the cheeks, forehead, and upper lip. This is melasma, a condition that not only affects luteal phase cycles but also emerges with hormone replacement therapy, thyroid imbalances, or the endocrine chaos of perimenopause.
The pattern is telling: melasma rarely appears on arms or hands. Instead, it clings to the central face, where oestrogen receptors are densest. Oral contraceptives, intrauterine devices, and certain antiepileptic drugs further prime this response. In Mzansi, summer’s high UV index does not initiate the condition, but it drastically accelerates its persistence.
For clinicians and patients, a practical assessment depends on correlating the symptoms with hormonal events rather than treating the surface alone:
– Recent pregnancy or lactational amenorrhoea
– Commencement or cessation of birth control pills
– Concurrent thyroid changes or cortisol spikes from stress
Each trigger alters the same pathway, yet the individual’s baseline skin pigment modulates the final severity. The result is a chronic, recurring condition that demands patience and a deep genomic audit, not just a corrective crepe.
Sun Exposure and Cumulative UV Damage
The South African sun is not a gentle benefactor. It is a relentless artisan, carving its signature into the dermis over decades. Each ray of high-index UV light does not merely tan; it delivers a memorandum of stress to the basal layer of the epidermis. The immediate response is a protective darkening, a surge of skin pigment meant to shield DNA from mutation. Yet, this defence is a double-edged sword, and the ledger of exposure never balances.
Cumulative UV damage operates with the patience of a slow tide. A single holiday in Cape Town or a working life in Pretoria’s highveld does not announce itself immediately. The evidence accrues invisibly, waiting for the fourth or fifth decade to surface as solar lentigines, the mottled whispers of the past. The melanocytes, once orderly, become erratic producers. They deposit flecks of skin pigment in uneven clusters, creating the texture of age spots and freckled shadows that refuse to fade.
The specific actions of the sun are precise and unforgiving:
– It fragments collagen, thinning the scaffolding that keeps tone even.
– It triggers an inflammatory cascade that signals melanocytes to overproduce.
– It disrupts the natural desquamation, trapping excess pigment in the upper layers.
These mechanisms are cumulative, meaning the damage is additive. The skin does not forget a single hour of unprotected exposure. For South Africans, this is a particular tragedy, as the annual UV index routinely reaches extreme levels. What begins as a golden glow in youth becomes a permanent, patchy architecture of skin pigment, a hieroglyph of every forgotten sunscreen application.
The irony is that the sun’s immediate effect is often aesthetically pleasing, which obscures the long-term cost. The body’s natural repair mechanisms become overwhelmed after years of assault, and the pigmentation becomes fixed, woven into the epidermal layers. This is why the texture of the skin changes; it becomes less about colour and more about the chaotic distribution of it. The threshold for damage is lower than most believe, and once crossed, the return to uniformity is a long and difficult march.
Post-Inflammatory Hyperpigmentation
Post-inflammatory hyperpigmentation does not appear without a reason. It follows an injury to the skin, and the trigger is often unremarkable. A squeezed pimple, an insect bite, or a minor abrasion can all spark a localized surge of skin pigment that settles into a stubborn dark mark. These marks are not random; they are the skin’s memory of a specific moment of trauma.
- Acne lesions, especially those that are squeezed or popped
- Burns from heat, chemicals, or excessive friction
- Cosmetic procedures such as chemical peels, microdermabrasion, or waxing
Each of these events disrupts the basal layer, prompting melanocytes to overcompensate. The result is an uneven tone that hugs the injury site. For many, the mark fades slowly, but repeated injuries create layers of excess skin pigment that become woven into the dermis. A single careless threading session or an aggressive scrub can begin the cycle anew.
Medications and Underlying Health Conditions
Certain prescription medications can quietly alter the way your body manages skin pigment! Antimalarials, often prescribed in South Africa for lupus and rheumatoid arthritis, may deposit a blue grey tone in the skin. Chemotherapy agents and tetracycline antibiotics can also trigger a patchy response. These reactions are not allergic in the classic sense, but they reflect a metabolic shift in melanin production.
Underlying health conditions add another layer. Addison’s disease, thyroid disorders, and chronic renal failure each disrupt hormonal signalling that governs melanocytes. When an internal system falters, the skin becomes a visible map of that imbalance.
- Antimalarials and antiarrhythmics are common culprits.
- Iron overload from repeated transfusions can darken the skin.
- Uncontrolled diabetes sometimes causes acanthosis nigricans.
The result is an uneven tone that appears without any external injury. For many patients, the first sign of a systemic problem is a change in skin pigment. Recognizing these triggers requires a careful look at a person’s full medical history, not just their skincare routine.
Professional Treatments and Clinical Procedures
Prescription-Grade Topical Agents
Melanin’s stubborn persistence often makes uneven tone a source of frustration. While daily care lays the groundwork, some discoloration requires a firmer hand. Professional treatments deliver potent active ingredients or targeted energy directly into the skin, disrupting cycles of excess production that home routines cannot easily break. This is where the expertise of a dermatologist becomes invaluable, as they tailor interventions to your specific skin type and pigment concerns.
Clinical procedures such as intense pulsed light or Q-switched lasers are precision tools. They seek out clusters of melanin and shatter them, allowing the body to clear the debris naturally. Similarly, professional peels using higher concentrations of alpha or beta hydroxy acids exfoliate the stratum corneum more aggressively, accelerating the turnover that reveals brighter, more even skin underneath. These methods offer a significant leap forward in managing both superficial and deeper pigment issues.
Following an in-office session, the focus shifts to prescription-strength topicals which are central to a long-term strategy. These formulations work in tandem with the in-office procedures to maintain results and prevent recalcitrant spots from returning.
– Hydroquinone (2-4%) works by inhibiting tyrosinase, the key enzyme in melanin production.
– Tretinoin accelerates cellular turnover and enhances the penetration of other lightening agents.
– Corticosteroids reduce the inflammation that can stimulate melanocyte activity.
This layered, synergistic approach is the gold standard for a reason. It addresses the biological mechanisms of pigment formation directly while the skin is most receptive. Ultimately, your dermatologist will craft a plan that safely and effectively reduces the contrast of hyperpigmentation, unveiling a more uniform and luminous complexion that reflects your skin’s inherent health.
Chemical Peels and Exfoliating Acids
Every minute, your skin sheds thirty thousand cells. A chemical peel accelerates this desquamation with clinical intent. In South African practices, professional peels deploy specific acids to address skin pigment. The most common are:
- Glycolic acid, harvested from sugar cane, for superficial peeling
- Salicylic acid, drawn from willow bark, for deep pore penetration
- Lactic acid, sourced from milk, for gentle hydration
Each acid loosens the intercellular cement of the stratum corneum. Dead keratinocytes lift away, revealing fresher layers. Multiple sessions allow used melanin to be shed rather than accumulated.
In my experience, patients observe visible change after the third session. This professional exfoliation works through a series of visits, each one removing subsequent layers and diminishing the contrast of persistent pigmentation. The result is a gradual rebalancing of skin pigment across the affected zones.
Laser Therapy and Intense Pulsed Light
In a single pulse of light, dermatologists can quiet the overactive melanocytes that have troubled patients for years. Laser therapy and intense pulsed light, or IPL, operate through selective photothermolysis. This process targets chromophores, the pigment-bearing structures within the skin, while leaving surrounding tissue unharmed.
South African practices commonly deploy Q-switched lasers for stubborn epidermal pigment and IPL for broader, diffuse discoloration. Both modalities fracture the clumps of skin pigment, which the lymphatic system clears over subsequent weeks.
Treatment intervals matter. A typical course spans four to six sessions, spaced three to four weeks apart, allowing skin pigment to resettle between visits.
Consider these distinctions when weighing options:
- Q-switched lasers deliver precise, high-energy pulses for isolated spots
- IPL emits scattered light, suitable for large facial areas
- Fractional lasers address textural change alongside pigment
Each approach demands skilled assessment. The clinician’s eye, not the machine, determines the outcome.
Microneedling and Radiofrequency
Patience is a scarce resource in any clinic, yet microneedling demands it. I have watched controlled needle trauma break down stubborn skin pigment, delivering results that lasers sometimes miss. Radiofrequency adds thermal precision, heating the dermis to remodel collagen and scatter pigment cells.
These procedures are not quick fixes. They require three to five sessions, spaced four weeks apart, to allow natural clearing mechanisms to work. The clinician adjusts needle depth and energy settings for each patient, targeting specific layers where discoloration lingers.
Combined with a disciplined home care routine, the outcome is a uniform tone that persists. The eerie part is how the skin continues improving months after the final session.
When to Consult a Board-Certified Dermatologist
Knowing when to seek professional help for a skin pigment concern can be the difference between a minor correction and a major medical intervention. While over-the-counter serums and diligent sunscreen use have their place, they often fall short against deep-seated melanin or complex conditions. A board-certified dermatologist possesses the diagnostic tools to differentiate between a harmless freckle, a stubborn patch of melasma, and something far more concerning. This distinction is critical, as your skin does not always reveal its internal struggles on the surface.
You should consider booking a consultation if you observe a sudden change in an existing mole or if a new spot appears with irregular borders or asymmetry. Professional evaluation becomes non-negotiable when pigment sits beneath the skin’s surface, presenting as a blue-gray or slate hue that topical agents cannot reach. Furthermore, if you have tried a consistent regimen for three months without visible improvement, you are likely losing ground against the pigment’s natural lifecycle. The clinic offers a higher magnification lens on your skin, literally seeing the layers that your mirror misses.
Clinical treatments are far more aggressive and precise than at-home care. A dermatologist might prescribe a compounded blend of hydroquinone, retinoic acid, and a corticosteroid to halt melanin production at the cellular level. They may also utilize specific energy-based devices, though the choice of laser wavelength or radiofrequency pulse depends entirely on your Fitzpatrick skin type to prevent post-inflammatory hyperpigmentation. In this setting, the provider adjusts the depth of penetration based on the specific chromophore they are targeting.
Here are the primary reasons to move from DIY to a doctor’s office:
– The pigment is spreading rapidly across your cheeks or forehead.
– You experience itching, bleeding, or tenderness in a pigmented area.
– Your skin has a history of adverse reactions to previous cosmetic procedures.
– The discoloration appears after starting a new medication.
Ultimately, the clinical environment offers a safety net that beauty counters cannot replicate. Treatments like a medium-depth peel or fractional resurfacing manipulate the dermis in ways that carry inherent risks, including infection or textural changes. A professional assesses your skin barrier integrity first, then curates a procedure list that addresses your specific pigment volume and depth. When you rely solely on a mirror, you miss the underlying biology; a clinic provides the expertise to manage that biology safely, ensuring your skin pigment journey remains a cosmetic one, not a medical crisis.
Targeted Skincare Ingredients for a More Even Complexion
Vitamin C and Ferulic Acid for Antioxidant Protection
The sun over Johannesburg is unforgiving, a fact your skin knows intimately. Your complexion’s fight against UV radiation is a relentless daily battle, and the front line is your skin pigment. Here is a compelling statistic: the synthesis of Vitamin C in human skin decreases by roughly 50% after just six weeks of chronic sun exposure.
This is where targeted antioxidants become your strategic allies. L-ascorbic acid, the purest form of Vitamin C, is a potent electron donor. It neutralises the free radicals that would otherwise trigger an overproduction of melanin, calming the very factories that create skin pigment. When paired with ferulic acid, a stabilising agent, the photoprotective power of Vitamin C doubles. This dynamic duo is essential for anyone serious about maintaining a clear, luminous appearance.
Consider what this synergistic formula achieves at the cellular level:
– It interrupts the oxidative stress cascade before it can stimulate melanocytes.
– It inhibits the activity of tyrosinase, the key enzyme responsible for pigment synthesis.
– It enhances the effectiveness of your sunscreen, providing a superior shield against environmental aggressors.
This approach focuses on prevention and interception. By dedicating the morning routine to these antioxidants, you are actively working to control the production of skin pigment and correct the visible signs of aging. This is not about a quick fix; it is about recalibrating your skin’s daily defence mechanism to ensure a uniformly bright and resilient tone.
Retinoids and the Acceleration of Cell Turnover
Niacinamide and the Role of Ceramides
Niacinamide stabilizes skin pigment by interrupting its transfer from melanocytes to keratinocytes. This direct action reduces the accumulation of colour in the upper layers. Ceramides, in parallel, reinforce the epidermal barrier. A strong barrier prevents moisture loss and calms the inflammatory signals that often intensify pigmentation.
Consider what niacinamide does at a cellular level:
- It limits pigment dispersion within the epidermis.
- It reduces the activity of inflammatory cytokines.
Ceramides work by filling the gaps between skin cells. Without sufficient ceramides, the barrier becomes compromised. Research indicates that skin pigment fades more predictably when ceramide levels are restored. The two ingredients work harmoniously, yet their pathways are distinct. Both are necessary for a complexion that reflects balance rather than damage.
Sunscreen: The Non-Negotiable Daily Defense
South Africa’s sun pushes the UV index past 10 on most clear days. That radiation is a direct threat to an even complexion. Sunscreen is the only daily step that actively intercepts the signal to produce excess skin pigment.
Without broad spectrum SPF 50, UVA penetrates deep into the dermis, triggering oxidative stress and an inflammatory response. Those signals travel to melanocytes, instructing them to overproduce. The result is a darker, uneven distribution of colour that is difficult to reverse.
Clinical studies confirm that consistent sunscreen use improves the efficacy of other targeted ingredients. It also reduces the need for corrective procedures. For anyone seeking a more even complexion, sunscreen is the essential daily step.
Lifestyle Modifications for Long-Term Results
Dietary Choices That Support Skin Health
The quiet victory against uneven skin pigment is often won in the kitchen and through daily rhythms, long before a cream ever touches the face. Your gut and your skin share a conversation that speaks in shades of brown and red, and what you place on your plate either soothes that dialogue or turns it into a shouting match. A diet rich in whole foods provides the raw materials for repair, while highly processed options can stoke the very inflammation that makes pigment cells overproduce.
Foods high in omega-3 fatty acids, such as sardines and snoek, can help to calm the cellular turmoil that triggers excess melanin. Meanwhile, an overload of refined sugar causes glycation, a process that stiffens collagen and can make the skin’s surface appear duller, forcing any existing pigment to look more pronounced. It is about building a steady, weekly pattern rather than seeking a perfect meal.
Antioxidants are the foot soldiers here, and their sources are wonderfully accessible. Look to the vibrant colours of local produce for support:
- Berries and dark leafy greens for anthocyanins and lutein.
- Orange vegetables like butternut and carrots for beta-carotene.
- Green tea, which offers polyphenols that interrupt the pigment pathway.
These compounds do not erase pigment, but they work to shield the skin’s DNA from oxidative stress, which is a primary trigger for new spots. The role of hydration also extends beyond water alone; consuming water-rich foods like cucumbers and watermelon supports the skin’s barrier function, ensuring that the outer layers are not easily irritated. A resilient barrier means less inflammation, which is a powerful ally in managing any form of skin pigment concern. Consider red rooibos, a local staple, for its aspalathin content, a flavonoid with notable anti-inflammatory properties that can be a gentle, daily addition to your routine.
Managing Stress and Prioritizing Sleep
One night of poor sleep can elevate cortisol by 21%, and that rise alone stimulates melanocytes to manufacture extra skin pigment. Over months, this persistent stress signal deepens uneven tone and slows repair. The skin’s overnight repair cycle, especially deep sleep, is when pigment cells return to baseline. Skimping on rest leaves them stuck in overdrive.
Stress management is a practical act. A walk in morning sun, a pause to breathe before meals, or a quiet minute with a cup of rooibos shifts the nervous system out of alert mode. These small intervals lower inflammation, allowing skin pigment to find equilibrium. Sleep hygiene is a consistent pattern: a cool bedroom, dim screens an hour before bed, and a fixed wake time. Consistency turns these fragments into a rhythm that protects your natural balance from within.
Avoiding Common Skincare Mistakes and Product Purgatories
The urge to overhaul everything is the most common skincare mistake. People abandon a routine during the purging phase, convinced the product is harming them. That phase is a temporary purge, often called a product purgatory, where deep pigment and dead cells surface before clearing. Another error is layering actives without considering pH and timing. The skin responds with irritation, which paradoxically worsens uneven tone.
- Swapping products weekly
- Exfoliating beyond tolerance
- Layering incompatible formulas
A steady protocol allows the epidermis to rebuild. Over months, this restraint produces stable skin pigment. You can feel your skin pigment settling into a calmer rhythm. Long term modification is not glamorous. It is the quiet consistency that your skin remembers.



0 Comments